CO2: The Number That Tells Your Doctor How Well You're Breathing and Buffering
When most people hear "carbon dioxide," they think of exhaled breath, greenhouse gases, or carbonated drinks. In the context of your blood panel, CO2 means something more specific and more medically important: it's a measure of bicarbonate — your blood's primary chemical buffer system.

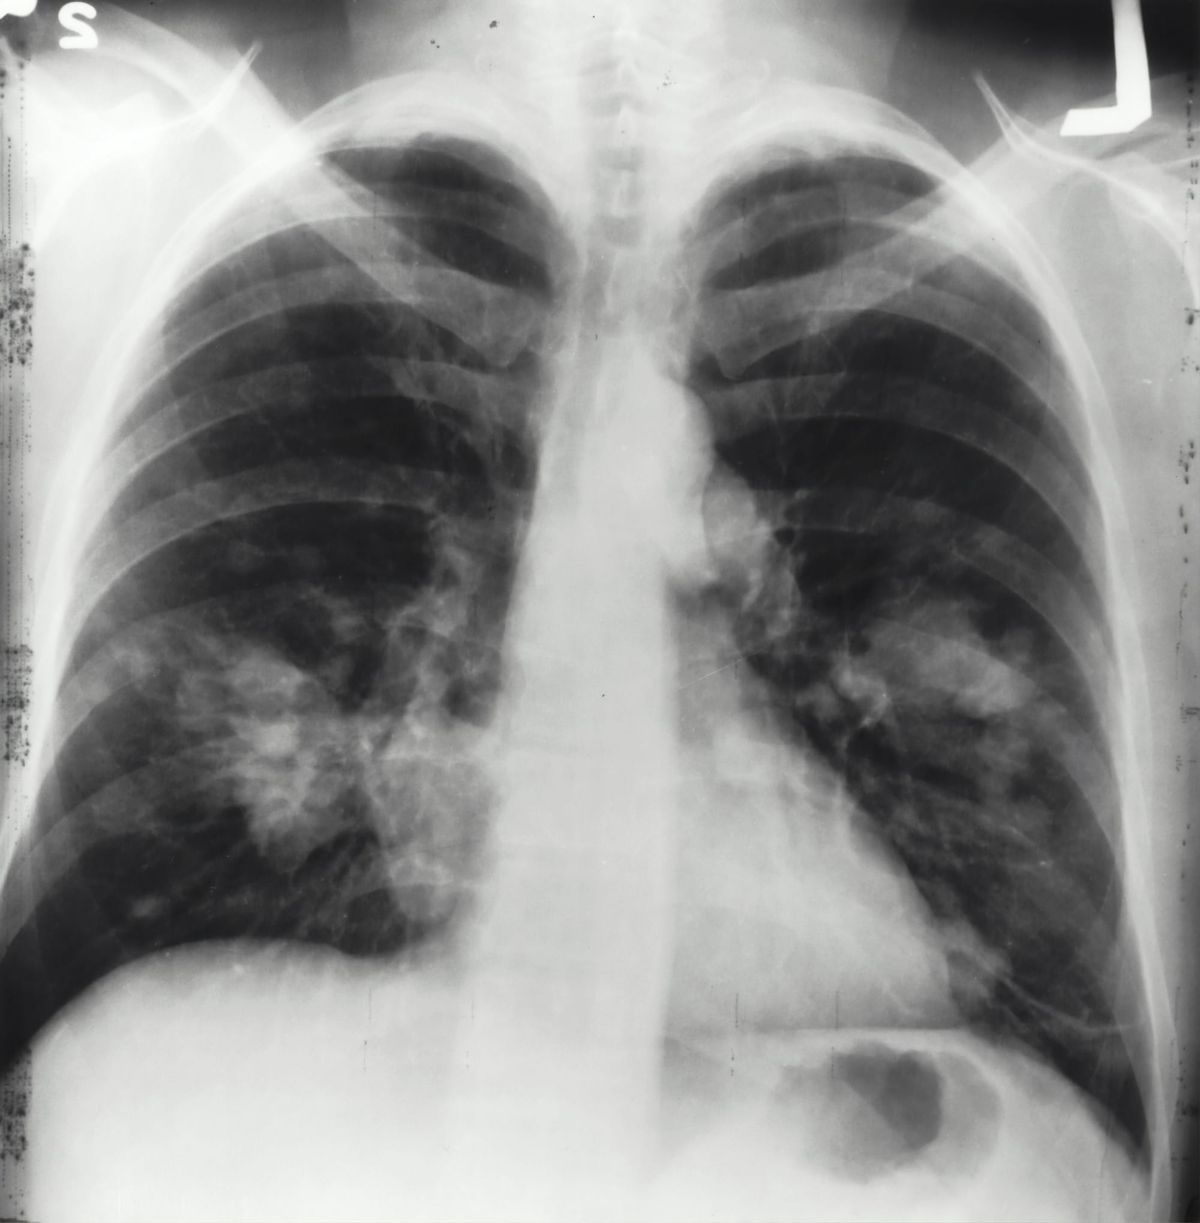
Carbon dioxide isn't just what you breathe out. In your blood panel, it's a window into the balance between your lungs and your kidneys — and what happens when that balance breaks down.
What Is It?
When most people hear "carbon dioxide," they think of exhaled breath, greenhouse gases, or carbonated drinks. In the context of your blood panel, CO2 means something more specific and more medically important: it's a measure of bicarbonate — your blood's primary chemical buffer system.
Here's the biology. Every cell in your body produces carbon dioxide as a waste product of energy metabolism. That CO2 dissolves into the blood, and most of it quickly converts into bicarbonate (HCO3-) — a process catalyzed by an enzyme called carbonic anhydrase. This bicarbonate travels through the bloodstream to the lungs, where it converts back into CO2 gas and is exhaled. The whole system works as a continuous chemical buffer, preventing your blood from becoming too acidic or too alkaline.¹
Your blood pH — the measure of its acidity — is one of the most tightly regulated parameters in the entire human body. It must stay within the narrow range of 7.35 to 7.45. Drift below 7.35 and you're in acidosis. Rise above 7.45 and you're in alkalosis. Either extreme disrupts enzyme function, protein structure, and cellular chemistry across every organ. Your lungs and kidneys are the two primary systems that maintain this balance — and the serum CO2 test is one of the primary ways your doctor monitors whether they're doing their jobs.²
What the CO2 test on your CMP actually measures is the total carbon dioxide content in your blood plasma — a value that reflects bicarbonate concentration (roughly 95% of the reading) plus a small contribution from dissolved CO2 gas. It is reported in milliequivalents per liter (mEq/L) and serves as a proxy for bicarbonate. When your doctor sees your CO2 number, they're largely reading your bicarbonate level — and using it to assess the acid-base status of your blood.³
Two organ systems are primarily responsible for your CO2 number. The lungs regulate CO2 quickly — within seconds to minutes — by changing breathing rate and depth. The kidneys regulate bicarbonate over hours to days by retaining or excreting it through urine. When one system struggles, the other compensates. A low CO2 on your blood panel can mean your lungs are blowing off too much CO2 (hyperventilation) or your kidneys aren't retaining enough bicarbonate — or both. A high CO2 typically means the opposite.
It's a quiet marker in many blood panels — easy to overlook when glucose and cholesterol are grabbing attention. But in the right clinical context, CO2 tells an important story about what's happening at the intersection of your metabolism, your breathing, and your kidneys.
What's the Healthy Range?
Serum CO2 (Bicarbonate) Reference Range:
- Normal: 22–29 mEq/L
- Low (potential metabolic acidosis): Below 22 mEq/L
- High (potential metabolic alkalosis): Above 29 mEq/L
Understanding what drives CO2 out of range requires knowing the four primary acid-base disorders:
Metabolic Acidosis (Low CO2):
This is the most clinically common reason to see a low CO2 on a standard blood panel. The body's bicarbonate reserves are being consumed trying to buffer an acid load — from diabetic ketoacidosis, lactic acidosis, kidney failure, severe diarrhea, or toxic ingestion (such as aspirin overdose or methanol). The lungs compensate by increasing breathing rate (hyperventilation) to blow off CO2 and reduce acidity. You may see low CO2 alongside an elevated anion gap.⁴
Metabolic Alkalosis (High CO2):
The body is retaining too much bicarbonate or losing too much acid. Common causes include prolonged vomiting (losing stomach acid), excessive diuretic use (which causes the kidneys to retain bicarbonate), overuse of antacids or bicarbonate-containing products, and primary hyperaldosteronism. The lungs compensate by slowing breathing to retain CO2 and restore pH balance.⁵
Respiratory Acidosis (High CO2):
The lungs aren't effectively clearing CO2 — it builds up in the blood, making it more acidic. Common causes include chronic obstructive pulmonary disease (COPD), severe asthma, obesity hypoventilation syndrome, and neuromuscular conditions that weaken breathing muscles. The kidneys compensate by retaining bicarbonate, which is why a chronically high CO2 can indicate a serious respiratory condition.⁶
Respiratory Alkalosis (Low CO2):
Hyperventilation — breathing too fast or too deep — blows off excess CO2, making the blood more alkaline. Common causes include anxiety and panic attacks, fever, high altitude, pain, and early sepsis. It's the most benign of the four disorders and often resolves when the underlying trigger is addressed.⁷
An important clinical note: a single CO2 reading slightly outside the normal range is not cause for alarm on its own. Context matters — what are the other electrolytes, kidney markers, and clinical symptoms doing alongside it? A CO2 of 20 mEq/L in someone with chronic kidney disease tells a very different story than the same reading in a healthy person who just finished a panic-inducing conversation before their blood draw.
What Can You Do About It?
CO2 is not a number you optimize through targeted supplements or a specific food protocol the way you might approach glucose or cholesterol. It reflects the body's pH buffering system, which is largely governed by kidney and lung function. For most healthy people, the best strategy is to support both those organ systems through broad lifestyle choices.
Supporting Healthy CO2 and Acid-Base Balance:
Dietary approaches that support alkaline buffering:
- Eat an abundance of vegetables and fruits — they produce bicarbonate precursors during metabolism and help maintain a more alkaline internal environment
- Potassium-rich foods (avocados, leafy greens, legumes, sweet potatoes) support kidney function and help maintain bicarbonate balance
- Reduce ultra-processed, high-protein, high-phosphate foods — these produce an acid load that the kidneys must buffer
- Adequate hydration supports kidney filtration and bicarbonate regulation
- Magnesium: plays a role in carbonic anhydrase enzyme function; deficiency can subtly impair CO2 processing
Breathing and exercise:
- Diaphragmatic (belly) breathing — slow, deep breaths — is the most direct way to optimize CO2 exchange in the lungs
- Regular aerobic exercise improves respiratory efficiency and the body's ability to manage CO2 production during increased metabolic demand
- Breath training practices (used in yoga, free diving, and the Wim Hof Method) can improve CO2 tolerance and breathing efficiency over time — though these practices should be approached with care and never done near water
- Manage anxiety and chronic stress — these are among the most common causes of habitual hyperventilation, which chronically lowers serum CO2 and can contribute to symptoms like fatigue, brain fog, and tingling extremities
Kidney health:
- Stay well hydrated — the kidneys need adequate fluid to regulate bicarbonate effectively
- Avoid nephrotoxic substances: NSAIDs (ibuprofen, naproxen) taken chronically, excessive alcohol, and contrast dyes damage kidney tubules that manage bicarbonate
- Control blood glucose and blood pressure — the two leading causes of chronic kidney disease, which progressively impairs bicarbonate regulation
If CO2 Is Consistently Abnormal:
Persistent CO2 outside the normal range warrants clinical investigation. Your doctor will likely order an arterial blood gas (ABG) — a more precise acid-base assessment — alongside kidney function tests, blood glucose, and a clinical review of symptoms and medications. Do not attempt to correct acid-base disorders through self-treatment. The underlying cause must be identified and addressed properly.
Bicarbonate supplementation (baking soda or sodium bicarbonate tablets) is sometimes used medically for specific types of metabolic acidosis — but only under physician supervision. Unsupervised use can cause metabolic alkalosis, electrolyte disturbances, and worsening of certain conditions.
The Science Right Now
CO2 and acid-base research is largely a clinical science, but several recent threads are worth knowing about — particularly for athletes and people with metabolic disease.
A 2022 study in the Journal of the American Society of Nephrology found that even mild, chronic metabolic acidosis — CO2 values in the low-normal range (22–24 mEq/L) over years — is associated with accelerated loss of kidney function, increased bone loss, and muscle wasting in people with early chronic kidney disease. This challenges the idea that being "within normal range" is always adequate, particularly for patients with existing kidney impairment.⁸
On the exercise science side, research published in Sports Medicine has reinforced what competitive athletes have long known: bicarbonate loading — consuming sodium bicarbonate before high-intensity exercise — can meaningfully buffer lactic acid accumulation and extend performance capacity in short-duration, high-intensity events. It works by temporarily raising serum bicarbonate, buffering the hydrogen ions produced during anaerobic metabolism. The effect is real, measurable, and used legally in competitive sports.⁹
Perhaps the most fascinating recent research involves CO2 and the brain. A 2023 study in Nature Neuroscience identified CO2-sensitive neurons in the brainstem (the retrotrapezoid nucleus) that directly regulate breathing rate based on blood CO2 levels. This chemoreceptor system is the body's primary breathing pacemaker — and dysfunction in it is now being investigated as a potential contributor to conditions like sleep apnea, sudden infant death syndrome (SIDS), and panic disorder, where CO2 sensitivity appears dysregulated.¹⁰
For those interested in going deeper on breathing physiology and CO2's role in human performance, Patrick McKeown's book The Oxygen Advantage is a highly accessible and research-grounded resource. McKeown's work on CO2 tolerance and nasal breathing has influenced training protocols across athletics, sleep medicine, and stress management.
"Most people think of breathing as oxygen in, carbon dioxide out. But the real story is CO2 — it's the primary driver of the urge to breathe, and learning to tolerate it better may be one of the most underrated performance and health interventions available." — Patrick McKeown, The Oxygen Advantage
The Bottom Line
Your CO2 reading is your blood's report card on acid-base chemistry — the invisible balancing act your lungs and kidneys are running 24 hours a day to keep your blood pH in the narrow zone where life works properly.
It won't tell you to change your diet or pick up a new supplement. What it will tell you is whether your respiratory and renal systems are communicating well — and whether something deeper needs attention.
If it's normal, support your kidneys with hydration and blood sugar control, support your lungs with movement and smart breathing, and let the system do what it was designed to do. If it's consistently off, don't ignore it. Ask why. The answer matters.
Your body's chemistry is not a mystery — it's a language. Learn to read it.
Sources & Endnotes
1. Hamm, L.L., Nakhoul, N., & Hering-Smith, K.S. "Acid-Base Homeostasis." Clinical Journal of the American Society of Nephrology, 2015. https://doi.org/10.2215/CJN.07400715
2. Hall, J.E. Guyton and Hall Textbook of Medical Physiology, 13th ed. Elsevier, 2016. Chapter 31: Acid-Base Regulation.
3. Kraut, J.A., & Madias, N.E. "Serum anion gap: its uses and limitations in clinical medicine." Clinical Journal of the American Society of Nephrology, 2007. https://doi.org/10.2215/CJN.00990207
4. Berend, K., de Vries, A.P., & Gans, R.O. "Physiological approach to assessment of acid–base disturbances." New England Journal of Medicine, 2014. https://doi.org/10.1056/NEJMra1003327
5. Gennari, F.J., & Weise, W.J. "Acid-base disturbances in gastrointestinal disease." Clinical Journal of the American Society of Nephrology, 2008. https://doi.org/10.2215/CJN.04050907
6. Roussos, C., & Koutsoukou, A. "Respiratory failure." European Respiratory Journal Supplement, 2003. https://doi.org/10.1183/09031936.03.00038503
7. Laffey, J.G., & Kavanagh, B.P. "Hypocapnia." New England Journal of Medicine, 2002. https://doi.org/10.1056/NEJMra012457
8. Raphael, K.L., et al. "Bicarbonate concentration, acid-base status, and mortality in the Health and Retirement Study." Journal of the American Society of Nephrology, 2022. https://doi.org/10.1681/ASN.2021040552
9. Siegler, J.C., & Marshall, P.W. "Sodium bicarbonate supplementation and exercise performance." Sports Medicine, 2022. https://doi.org/10.1007/s40279-022-01675-4
10. Souza, G.M.P.R., et al. "Brainstem CO2-sensitive neurons and respiratory chemoreception." Nature Neuroscience, 2023.
© Commit250 | commit250.com | All articles in this series are for informational purposes only and do not constitute medical advice. Consult a qualified healthcare provider before making changes to your diet, supplements, or exercise routine.